
How Botulinum Toxin Works and What Happens After the Injection
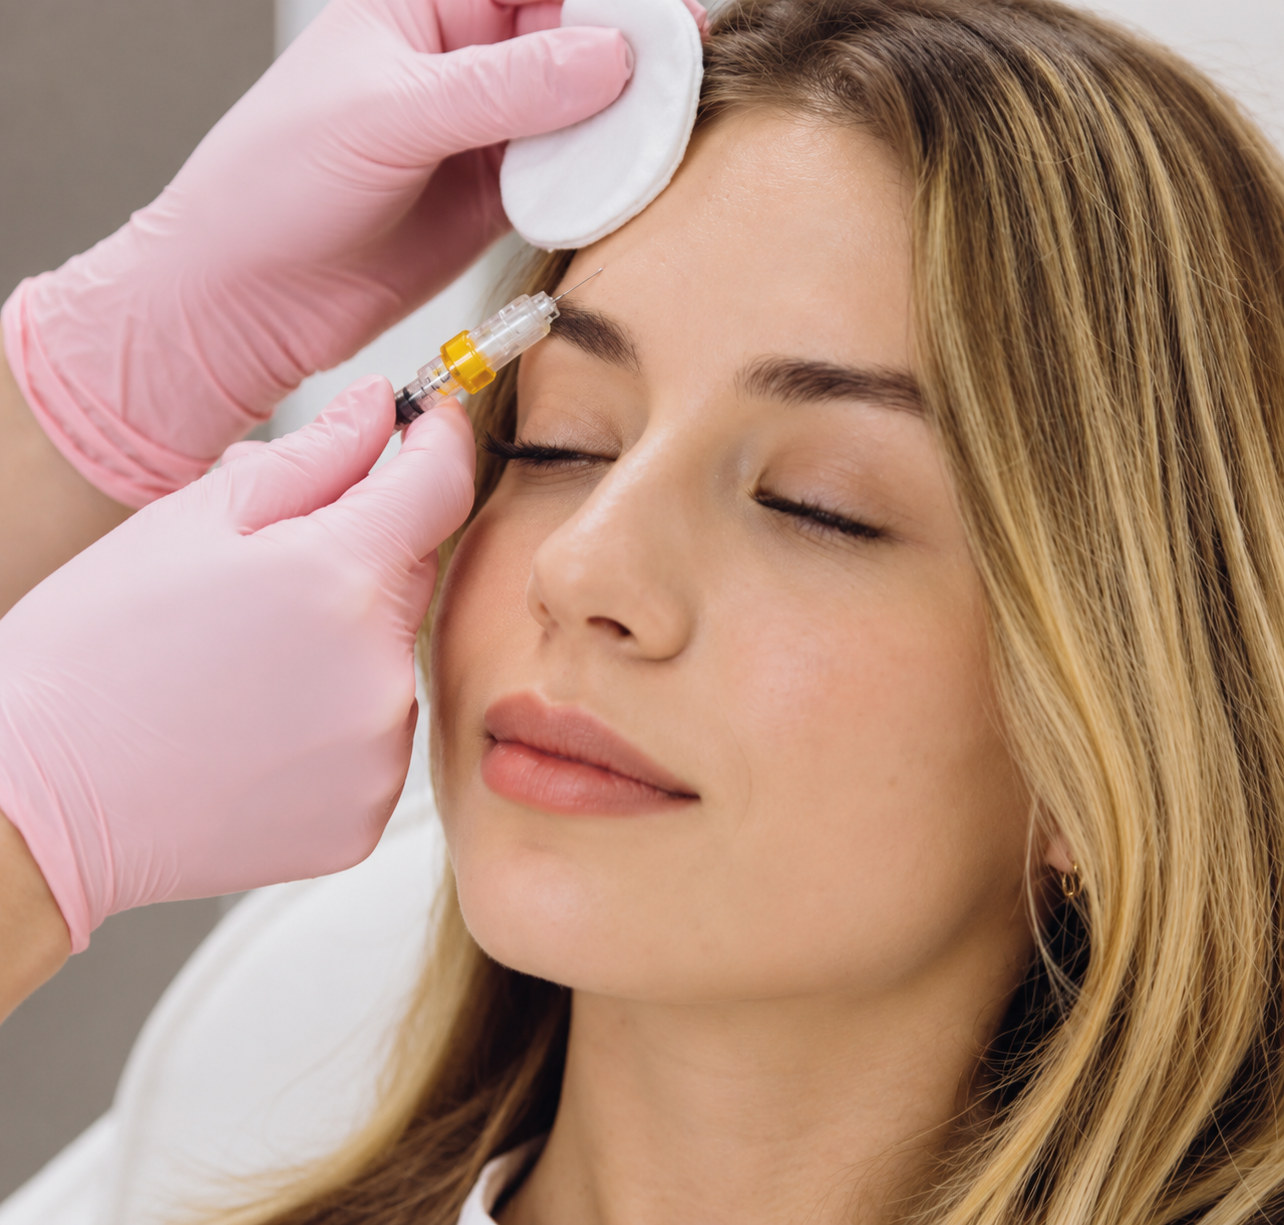
Botulinum toxin is the single most requested aesthetic treatment in the United States, and it is also the treatment patients understand least accurately. Most arrive with a mental model built from social media, where the product is described as something that freezes muscles or fills lines. Neither is correct. Understanding what the molecule actually does at the nerve terminal changes how a practice talks to patients, how it schedules follow up, and how quickly staff recognize the difference between a normal response and a problem.
This article covers the mechanism, the timeline, the treatment areas, and the support role that an Aesthetic Medical Assistant (AMA) plays around a neurotoxin appointment. Injection itself is a delegated medical act performed by a licensed prescriber or a licensee operating under supervision, and the rules for who may inject differ by state.
The mechanism at the nerve terminal
Botulinum toxin type A is a protein produced by Clostridium botulinum. In its purified pharmaceutical form it is injected in extremely small quantities into a specific muscle. Once it reaches the neuromuscular junction, the toxin binds to the motor nerve terminal and is taken inside the cell. There it cleaves SNAP-25, one of the SNARE proteins that allow vesicles filled with acetylcholine to fuse with the nerve membrane and release their contents into the synaptic gap.
Without acetylcholine crossing that gap, the muscle fiber receives no signal to contract. The muscle itself is untouched and structurally normal. It is the message that stops, not the tissue. This distinction matters when a patient asks whether the treatment damages the muscle permanently, and it also explains why the effect wears off. Over the following weeks the nerve terminal grows new sprouts and re establishes functional contact with the muscle, and the original terminal eventually recovers. Signaling returns and so does movement.
Because the drug works on dynamic movement rather than on volume, it addresses lines that appear when a patient animates. Lines that are visible when the face is completely at rest have usually become etched into the dermis and respond only partially, and often need resurfacing, microneedling or a filler alongside the toxin. Setting that expectation before the first syringe is drawn prevents most of the disappointment calls a practice receives in week three.
The timeline patients need to hear before they leave
Nothing happens on the day of treatment beyond small injection bumps that settle within twenty minutes. The first change in movement typically appears around day three to five. Effect builds through day ten to fourteen, which is when the result should be assessed and when any touch up is decided. Most practices book that review appointment at the time of treatment rather than waiting for the patient to call, because a patient who is unhappy on day six will often post about it before day fourteen arrives.
Duration in the glabella and forehead is commonly three to four months, though a patient with strong musculature, a high metabolic rate, or a history of frequent treatment at low doses may notice movement returning sooner. Longer intervals between sessions do not weaken the result over time, but consistent treatment often allows the prescriber to maintain the same effect with slightly fewer units as the habit of over animating fades.

Approved areas and the areas patients ask about anyway
In the United States, the cosmetic indications approved by the FDA across the type A products cover glabellar lines, lateral canthal lines, and forehead lines, with product specific variation. Axillary hyperhidrosis and chronic migraine carry separate therapeutic approvals for onabotulinumtoxinA. Everything else that a med spa performs with a neurotoxin, including masseter reduction for jaw slimming, platysmal bands, the lip flip, gummy smile correction, chin dimpling and microdosed intradermal techniques, is prescribed off label.
Off label is a legal and clinical category, not a warning label. Physicians may prescribe an approved drug for an unapproved indication when the clinical judgment supports it. What staff must avoid is describing those uses to patients as approved treatments, or implying in marketing copy that the FDA has cleared a product for masseter slimming. That is a compliance exposure and it is one of the easier ones for a state board or the FTC to identify from a website.
Units, dilution and why the numbers do not transfer
A unit of botulinum toxin is defined by the biological activity of that specific product, not by weight or volume. Twenty units of one brand is not twenty units of another. Dilution is a separate variable chosen by the prescriber, and it changes the volume delivered per injection point and therefore how far the product spreads through the tissue. A more dilute preparation covers a wider field, which is useful in the forehead and risky near the orbital rim.
Support staff who reconstitute product under supervision, where state rules allow it, should treat dilution as a documented recipe rather than a habit. Saline type, volume, gentle introduction of the diluent down the vial wall rather than a forceful jet, and the time and date of reconstitution all belong in the log. A vial reconstituted at nine in the morning and used at four in the afternoon is a different clinical object from one drawn up minutes earlier, and if a result underperforms, the log is the only way to find out why.
Where the assistant role actually sits
The visible part of a neurotoxin appointment lasts about ten minutes. Everything that determines whether it goes well happens around it. The assistant confirms the medical history and specifically asks about neuromuscular conditions, pregnancy and breastfeeding, aminoglycoside antibiotics, recent treatment elsewhere and the date of it, and any history of ptosis after a previous session. The assistant takes standardized photographs at rest and in full animation, using the same lighting, the same distance and the same expressions every time, because inconsistent photography is the reason most before and after comparisons prove nothing.
During the appointment the assistant prepares the tray, applies ice or topical anesthetic if the protocol calls for it, and positions the patient upright. Afterward the assistant delivers post care and documents that it was delivered. The instructions patients most often get wrong are lying flat or having a massage in the first four hours, going straight to a hot yoga class, and rubbing the treated area while removing makeup that evening. Explaining why each instruction exists produces far better compliance than reciting a list.
Adverse events and when to escalate
Bruising and small wheals at injection points are expected. Headache in the twenty four hours after glabellar treatment is common and self limiting. The findings that need the prescriber, not reassurance, are eyelid ptosis appearing in the first two weeks, brow heaviness that interferes with vision, meaningful asymmetry after day fourteen, diplopia, difficulty swallowing, and any generalized weakness. The last three are rare but they are the ones that must never be triaged by a non licensee.
A practice benefits from a written escalation rule that removes judgment from the moment of panic. Any patient reporting a visual change, a swallowing change or weakness beyond the treated area is routed to the prescriber the same day and the contact is documented. Everything else gets a photograph, a note and a scheduled review. Staff who know exactly where the line sits escalate earlier and more calmly than staff who are asked to decide what counts as serious.
State variation
Who may inject a neurotoxin, who may reconstitute it, whether a good faith examination must be performed in person or may be done by telehealth, and whether a medical director must be physically present are all determined at state level. Some states permit registered nurses to inject under delegation with a chart review, others require the prescriber to have personally evaluated the patient during that visit. Medical assistants are excluded from injecting in most states regardless of training or certification. Verify the current rule with the state medical board and the state nursing board rather than with a training vendor, because vendors sell courses in states where the graduate cannot legally use them.
Neurotoxins sit at the center of almost every aesthetic practice in the country, which means the clinical support team touches them daily.
If there are topics you would like to see covered next, write to us at editorial@upsthetics.com.
This article is educational and does not constitute medical advice, diagnosis or treatment guidance. Scope of practice, delegation and supervision requirements vary by state and change over time. Always verify current requirements with your state licensing board and follow the protocols set by your supervising physician.
FAQS
How long does botulinum toxin take to work?
Movement usually begins to change around day three to five, with the full effect visible at day ten to fourteen. Any assessment or touch up decision should wait until day fourteen.
Does botulinum toxin fill wrinkles?
No. It reduces the muscle contraction that creates dynamic lines. Lines visible at complete rest are an issue of dermal quality and volume, and are treated with other modalities.
Are units interchangeable between brands?
No. A unit reflects the biological activity of that specific product. Dosing is determined by the prescriber for the product being used and cannot be converted casually between brands.
Can a medical assistant inject botulinum toxin?
In most states, no. Injection of a prescription drug is a delegated medical act restricted to specific licensees. Scope rules are set at state level and must be confirmed with the relevant board.
Why does the effect wear off?
The nerve terminal recovers. New nerve sprouts re establish contact with the muscle and normal signaling returns, typically over three to four months in the upper face. Before you go
Stay Updated
Related posts

Pressotherapy for lymphatic drainage: benefits, safety considerations, and professional use
How Platelet Rich Plasma and PRF Are Prepared and Used in Aesthetic Practice

What facial contouring actually means in a medical aesthetic practice
About the author
